Condition
Shoulder Pain After a Car Accident
Seatbelt restraint forces, bracing impacts, and airbag deployment can all injure the shoulder complex. From rotator cuff tears to labral damage, accurate diagnosis determines both your treatment path and the strength of your case.
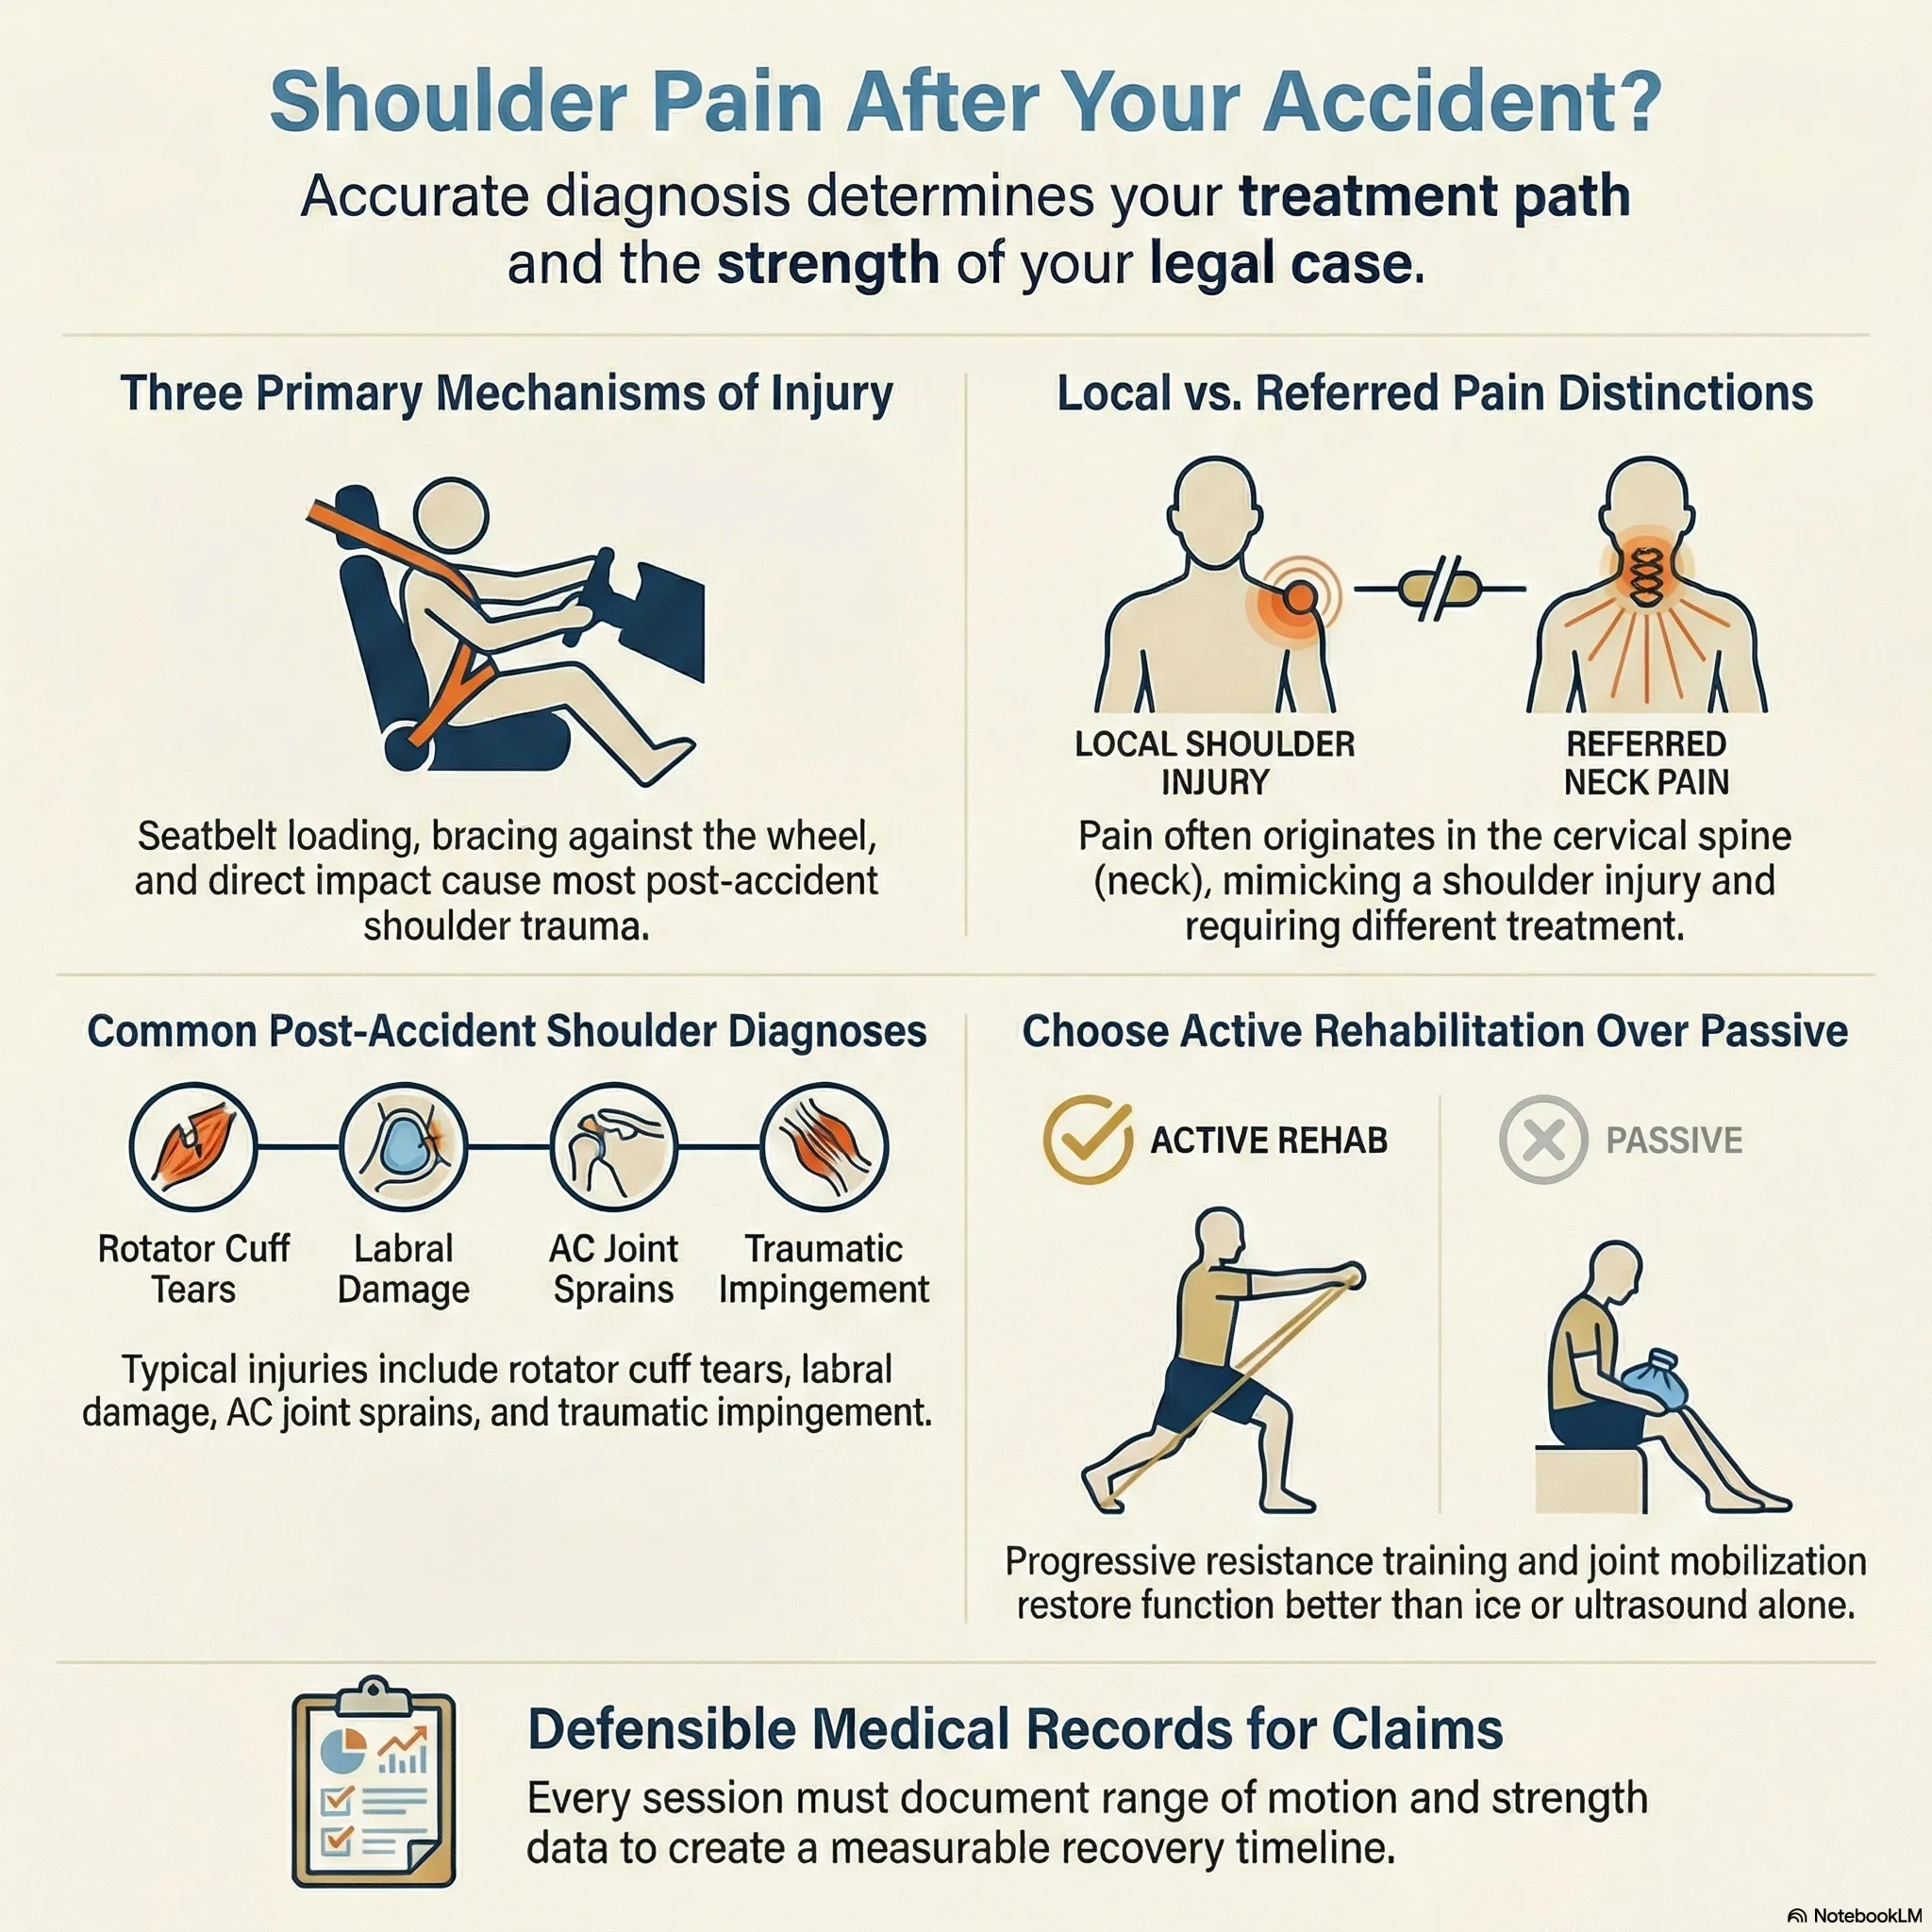
Shoulder pain after a car accident can come from the seatbelt loading the shoulder, from bracing your arms against the wheel, or from a neck injury that sends pain into the shoulder. At our Petaluma clinic, Dr. Lloyd tests the rotator cuff and labrum by hand and screens your neck in the same visit.
Go to an emergency room or call 911 if you have:
- Sudden pressure or crushing pain in your shoulder
- Pain spreading from your chest to your left jaw, arm or neck
- Shoulder or chest pain with shortness of breath, dizziness or sweating
- A very painful shoulder right after the crash
- A shoulder that is swollen, bruised or bleeding after the crash
If none of these apply, book an evaluation this week at our Petaluma clinic or call (707) 658-2534.
Sources: MedlinePlus, Shoulder pain.
Understanding the Injury
What Causes Shoulder Pain After an Accident?
The shoulder is the most mobile and least stable major joint in the body. This makes it uniquely vulnerable to the forces generated in a car accident. Three primary mechanisms cause shoulder injuries during collisions: seatbelt loading, bracing against the steering wheel or dashboard, and direct impact from airbag deployment or door intrusion.
The diagonal path of the seatbelt across the chest and shoulder concentrates enormous deceleration forces on the clavicle, AC joint, and rotator cuff. Drivers who brace against the steering wheel transmit collision forces directly through their extended arms into the shoulder joint. Side impacts can drive the door panel into the shoulder, causing direct trauma to the joint complex.
An Important Distinction: Local vs. Referred Pain
Not all shoulder pain after a car accident originates in the shoulder itself. Cervical spine injuries, particularly disc herniations at C4-C5 and C5-C6, can produce referred pain that mimics shoulder pathology. This is why our examination always includes a cervical spine evaluation alongside the shoulder assessment — ruling out neck pain as a contributing source.
Differentiating between a true shoulder injury and cervical referred pain is critical. It changes the diagnosis, the treatment plan, and the documentation strategy for your case. A missed cervical contribution to shoulder pain can undermine both your recovery and your legal claim.
Rotator Cuff Injuries
The four rotator cuff muscles (supraspinatus, infraspinatus, teres minor, subscapularis) can be strained, partially torn, or fully torn by collision forces. Seatbelt loading is a particularly common mechanism.
Labral Tears
The labrum, a ring of cartilage that deepens the shoulder socket, can be torn when the arm is forced into extreme positions during impact. SLAP lesions and Bankart lesions are common post-accident findings.
AC Joint Injuries
The acromioclavicular joint connecting the clavicle to the shoulder blade is vulnerable to direct impact and seatbelt forces. Sprains range from mild stretching to complete ligament disruption with visible deformity.
Shoulder Impingement
Post-traumatic inflammation and swelling narrow the subacromial space, pinching the rotator cuff tendons and bursa during overhead movements. Produces pain with reaching, lifting, and sleeping on the affected side.
Referred Pain from Cervical Spine
Cervical disc herniations and nerve root compression at C4-C6 can produce pain in the shoulder and upper arm that closely mimics a primary shoulder injury. Proper differential diagnosis is essential.
Diagnosis
How We Diagnose Shoulder Pain
A comprehensive shoulder evaluation combined with cervical spine screening to identify the true source of pain and document every finding.
Orthopedic Shoulder Testing
Systematic evaluation using provocation tests specific to each shoulder structure potentially injured.
- Shoulder range of motion (goniometry)
- Empty can test (supraspinatus)
- External rotation lag sign (infraspinatus)
- Lift-off test (subscapularis)
- O'Brien's test (labral pathology)
- Cross-body adduction (AC joint)
Cervical Spine Screening
Every shoulder evaluation includes cervical assessment to identify referred pain from the neck.
- Cervical range of motion
- Spurling's test for radiculopathy
- Shoulder abduction relief sign
- Upper extremity neurological exam
- Dermatome and myotome testing (C4-T1)
- Deep tendon reflex assessment
Imaging & Functional Assessment
Advanced imaging coordination and objective functional measurement when clinical findings warrant.
- MRI referral for rotator cuff and labrum
- X-ray for AC joint separation grading
- Shoulder strength testing (dynamometry)
- Functional reaching and lifting capacity
- Clinical-imaging correlation documentation
- Impingement and instability classification
Treatment
How We Treat Shoulder Pain
Progressive rehabilitation targeting the specific injured structures. We work on shoulder function through graded loading, stability training, and tissue recovery.
Progressive Resistance Training
Rebuilds rotator cuff strength, scapular stability, and shoulder girdle endurance. We use carefully graded resistance exercises progressing from isometric holds through concentric and eccentric loading to build the dynamic stability the shoulder requires for normal function.
Rotator Cuff RehabilitationVibration Therapy
Vibration training hasn't been studied for shoulder injuries after a crash. Standing on the platform mainly works the legs and trunk, so for the shoulder it plays a small, supporting part alongside shoulder exercise.
Shoulder Stability RetrainingShockwave Therapy
For calcium deposits in a rotator cuff tendon, trials found shockwave eased pain, and the deposits often shrank or cleared. For other rotator cuff pain, trials found little or no benefit over a sham, and it hasn't been studied after a car crash.
Calcium DepositsChiropractic Care
Hands-on care for the shoulder and the neck: gentle mobilization of the shoulder and AC joints, and adjustments when your neck is part of the pain. Right after a neck adjustment, many people with neck pain feel less pain and tenderness and can turn their head further. We use this hands-on care alongside your shoulder exercises.
Joint MobilizationDocumented Recovery Timeline
Every session generates objective data: shoulder range of motion measurements, rotator cuff strength testing, functional reaching and lifting capacity, and pain ratings during specific activities. This progressive documentation creates the measurable recovery timeline required for personal injury cases, from baseline deficits through treatment response and maximum medical improvement.
Defensible Medical RecordsWhy adjust.clinic
What Makes Us Different
Shoulder injuries after car accidents require a provider who evaluates both the shoulder and the cervical spine, treats with progressive rehabilitation, and documents everything for your case.
-
QME Designation
Dr. Lloyd's Qualified Medical Evaluator certification means his shoulder injury diagnoses, treatment necessity opinions, and impairment ratings follow state-tested AMA Guides and report-writing standards.
-
Cervical-Shoulder Differential
We always evaluate the cervical spine alongside the shoulder to determine whether pain is local, referred, or both. This distinction is critical for accurate diagnosis, effective treatment, and defensible documentation.
-
Active Rehabilitation
Passive therapies like ice and ultrasound don't rebuild rotator cuff strength. Our progressive resistance approach aims to rebuild the dynamic stability and functional capacity the shoulder needs for daily activities.
-
Seatbelt Injury Documentation
We understand and document the specific mechanism of seatbelt-related shoulder injuries, connecting the restraint forces to the clinical findings in a way that supports causation analysis for your case. Our documentation meets the standards personal injury attorneys require.

Common Questions
Frequently Asked Questions About Shoulder Pain After a Car Accident
How does a car accident cause shoulder injuries?
Shoulder injuries in car accidents typically result from bracing against the steering wheel on impact, seatbelt loading across the shoulder, or direct contact with the door panel or window in side-impact collisions. The sudden force can tear rotator cuff tendons, damage the labrum, strain the AC joint, or cause shoulder impingement from inflammatory swelling.
What's the difference between a rotator cuff tear and a labral tear?
The rotator cuff is a group of four tendons that stabilize and move the shoulder — tears cause pain with overhead movement and weakness. The labrum is a cartilage ring that deepens the shoulder socket — tears cause clicking, catching, a feeling of instability, and deep joint pain. Both injuries commonly occur in car accidents and require different treatment approaches. MRI with contrast is often needed to distinguish between them.
Do I need surgery for a shoulder injury from a car accident?
Surgery is typically only considered for complete rotator cuff tears, significant labral tears with recurrent instability, or fractures. For other shoulder injuries, care starts with graded shoulder exercises and hands-on care, and shockwave is an option for calcium deposits in a rotator cuff tendon, where trials support it. Ryan Lloyd, DC, QME, examines your shoulder and neck first to decide on a treatment path, and refers you for a surgical opinion when needed.
Can I get an impairment rating for a shoulder injury from a car accident?
Yes. Shoulder injuries that result in permanent loss of range of motion, strength deficits, or chronic instability can qualify for impairment ratings under the AMA Guides. Dr. Lloyd documents your shoulder function throughout treatment and, when appropriate, provides impairment ratings that support the value of your personal injury claim.
How long does shoulder pain treatment take after a car accident?
Mild shoulder strains typically resolve in 4-8 weeks. Rotator cuff injuries and AC joint sprains may take 8-16 weeks. Labral tears and complex shoulder injuries can require 4-6 months to reach maximum medical improvement. Early treatment and consistent rehabilitation support your recovery. Tendons and ligaments heal more slowly than muscle because they have a poorer blood supply; our guide to how soft tissue heals compares them.
Shoulder pain from your accident?
Get a comprehensive evaluation that covers both the shoulder and cervical spine. Same-week appointments available.
Have MedPay on your auto insurance? Learn how to use it here.
Learn more about our car accident chiropractic care in Petaluma.
Related Conditions
Other Conditions We Treat
Shoulder injuries frequently co-occur with cervical spine and upper back injuries. Explore the other accident-related conditions we focus on.